timeswww.8090.com
www.8090.com 时间:2021-03-21 阅读:()
InternationalJournalofObesity(2008)32,S1–S22008NaturePublishingGroupAllrightsreserved0307-0565/08$30.
00www.
nature.
com/ijoPLENARYLECTUREST1:PLWillthehumangenomegiveustheanswertoobesityAdebate–thecasefor.
PFroguelMD,PhD,GenomicMedicine,HammersmithHospital,ImperialCollegeLondon,UKandCNRS8090-InstituteofBiology,PasteurInstitute,Lille,FranceObesityhasbeenconsideredaparadigmformanyofthecommonchronicnoncommunicablehumandiseasesoftheglobalization,whichgenerallyresultwhenmultipleinheritedsusceptibilityvariantsinteractwiththe'Westernised'environmenttomodulatediseasepredisposition.
Recentlargescaletwinstudiesconfirmedtheimportantroleofinheritedfactorsinthedevelopmentofobesity.
Furthermore,anonnegligiblefractionofearlyonsetsevereobesitycasescarryDNAdefectsinasinglegeneresultingindramaticallyimpairedappetiteregulation.
These(ratherunexpected)discoverieshavegreatlyimprovedourunderstandingoftheroleontheenergybalanceoftheleptin-melanocortinpathwayinhumans.
RecentanalysesoftheimpactofMC4-Rnonsynonymousmissensemutationsinlargepopulationshaveshownthatbothlackandgainoffunctionexist,leadingtoeithersevereobesityorasignificantprotectionagainstoverweight.
However,eveninthismodeltheenvironmentmaymodulatetheobesityphenotype.
Polygenicobesitygeneticsisstillpoorlyunderstoodbutpastandon-goinggenomewidestudiesbringnewharvestofgenesandlocithathavebeenproventoincreasetheriskforobesity.
Inthisregard,therecentdiscoveriesoffrequentDNAvariants(SNPs)inthehypothalamusexpressedFatmassandObesityassociatedFTOandProconvertase1(PCSK1)genesandintheMC4-Rregulatoryregionevidencethatproteinsinvolvedinfoodintakebehaviourregulationareindeedcontributingtothedevelopmentofobesityinhumans.
ApartfromfrequentSNPs,itislikelythatmanyraremutations,copynumbervariationandepigeneticfactorsinthesegenesandinothersmayparticipatetoobesitypathophysiology.
TheemergingpictureofobesitymolecularmechanismincludesdifferentgeneticmechanismsincludingallelicselectionintheNeolithicage,theaccumulationofpathogenicraremutations,aswellasthestrongeffectofrecentobesegenicpressureon"thriftygenes"ancestralalleles.
Elucidatinggeneticeffectsshouldnotonlybringnovelandunsuspectedhypothesesbutwillalsosupportepidemiologicalstudiesinordertodifferentiateetiologicalandconfoundingfactors.
WillthehumangenomegiveustheanswertoobesityAdebate–andthecaseagainst.
HeitmannBLInstituteofPreventiveMedicine,CentreforHealthandsociety,CopenhagenDenmarkObesityisunderstronggeneticinfluence.
AdoptionstudiesshowthatadultbodymassindexamongadopteesishighlycorrelatedwithBMIofbiologicalparentsbutnotofadoptiveparents.
Inaddition,twinstudiesalsoshowthatgeneticpredispositiontoobesityaccountsformostofthefamilialcorrelationinobesityandabdominalfatdistribution.
Suchstudiessuggestthatthehumangenomeplaysanessentialroleforobesity.
However,environmentalinfluencesalsoplayaroleandinteractwiththegeneticpredispositiontoproduceobesity,andtheindividualdifferencesinobesitydevelopmentsuggestthatnotallvariationinobesitycanbeattributedtothegenes.
Also,theverylargedifferencesseenamongsocialclassesintheoccurrenceofobesity,withprevalences5timeshigheramonggroupswithlowcomparedtohighsocioeconomicstatus,suggestthatthegeneticpredispositionismodifiable.
Itisarguedthatobesityisageneticdiseaseexpressedonlywhentheenvironmentsupportsitsoccurrenceandcognitivesuperstructuresarenotoperating,andthatthehumangenomewillnotgiveustheanswertoobesity.
T2:PLFor:HowUsefulareClinicalGuidelinesforWeightManagementLeanMEJUniversityofGlasgowandUniversityofOtagoDatingfrom1996(SIGN),obesityguidelinesintegratetreatment(weightloss,avoidinggain,optimalrisk-factormanagement)withprevention,withinhealthcareservices,population-directedhealth-promotionandmodifyingobesogenicfood-,physical-,educational-andfiscal-environments.
Towarrantaguideline,animportanthealthproblemisperceivedassuboptimallyorinconsistentlymanaged,withneedtoprotectpatientsfromhazardousorineffectivetreatments,orfromfailure-to-treatwhenevidenceispositive.
Commonly,treatmentsarenotdirectlycomparablewithinpatients(egdiet,drugs,surgery)andhead-to-headtrialslacking,soguidelinestaketheformofalgorithms.
Preventionguidelinesoftenlackexperimentalorevengoodobservationaldatabutaimtohelppolicy-makersfromanunderstandingofunderlyingscientificprincipleswhenmuchmisinformationiscirculatingandresourcesscarce.
Methodologiestoproduceconvincingevidence-basesoftenlagbehindneedforguidance,sotheirfirst'usefulness'isineducatingtheirexpertwritersandcommissioningagencies.
Obesityguidelineshavenotyetgeneratedreducedprevalence,orsecondarydiseases.
Thisaspirationwasinappropriate,astime-coursesfrompublicationtochangingpracticearelong,andthediseaseevenlonger.
Usefulnesscanbegaugedearlierfromacademiccitations–egc.
150forSIGN1996,frommentionswithinotherclinicalguidelines(egCHD,diabetes,venousthrombosis,asthma,arthritis).
Secondarycareconsultantsnowagreetomanageobesitywithinc.
30%ofdiversespecialties.
About70%ofGPsandnursesreadtheSIGNobesityguideline,anditsrecommendationtorecordheight/weightnowformsnormalpractice.
Governmentpublic-healthstrategieshavebeeninformedbySIGNclinicalguidelines,callsforactionbeingstrengthenedbyconsistencyofsimilarguidelinesinternationally.
Against:HowusefulareclinicalguidelinesforobesitymanagementMercerSWUniversityofGlasgow,Glasgow,Scotland,UKObesityisgloballyregardedasamajorpublichealthissue.
Chronicdiseasemanagementinmanycountries,includingtheUK,isincreasinglybeingdeliveredinprimarycareusingprotocolsbasedonclinicalguidelines.
WhynotaddobesitytothegrowinglistofconditionsnowbeingtreatedbysuchanapproachAlthoughsuperficiallyattractive,thereareanumberofreasonstobelievethatrelyingsolelyonclinicalguidelinesforobesitymanagementisdoomedtofailure.
Firstly,despitedecadesofresearch,theevidence-baseforeffectiveandpracticalinterventionsforobesityisperhapssurprisinglysomewhatlimited,andthequalityandbreadthofstudiesusedtodevelopguidelinesequallylimited.
Morefundamentally,the'gold-standard'ofclinicalguidelineevidence-base,therandomisedcontrolledtrial,producesevidencebasedonoftenhighlyselectedsub-groupsofpatientswhichisthusofunknownrelevancetothebulkofthepopulationwiththetargetcondition.
Secondly,systematicreviewssuggestthattheissuingofclinicalguidelinesoftenfailstochangepractice.
Thirdly,themanagementofcomplexconditionssuchasobesityrequirescomplexinterventions,underpinnedbytheorythatembracessuchcomplexity,whichfurthermitigatesagainsttheusefulnessofsimpleguidelines.
Obesitymanagementisalsoinfluencedbyahugerangeofimportanthuman,system,andenvironmentalfactors.
Noclinicalguidelinecanleadpatientanddoctorthroughthelabyrinthofdecisionsthatneedtobemadeinprioritisingandtargetingwhichproblemtoaddressfirstandhow–onlyindividualisedcare,clinicalwisdomandshareddecisionsbasedontherapeuticrelationshipscantacklesuchcomplexity.
AbstractsS2InternationalJournalofObesityT3:PLWhyaclusterisreallyacluster:insulinresistanceandcardiovasculardiseaseReaven,GStanfordUniversitySchoolofMedicineThreesetsofdiagnosticcriteriahavebeenproposedtoidentifyindividualswithwhathasbeentermedthemetabolicsyndrome(MetS):WHO,ATPIII,andtheIDF.
Thegoalistoidentifyindividualsatincreasedcardiovasculardisease(CVD)risk,andthesamecomponentsareusedtomakethediagnosis.
However,thethreeorganizationsdifferintheirapproachtodiagnosingtheMetS.
TheWHOrequiresthatevidenceofinsulinresistancebepresentinordertomakeadiagnosis,whereastheAmericanHeartAssociationandtheNationalHeart,Lung,andBloodInstitute,focusedontheATPIIIcriteria,statethattheMetS"istrulyasyndrome,i.
e.
,agroupingofASCVDriskfactors,butonethatprobablyhasmorethanonecause.
"Incontrast,theIDFstatesthat"centralobesity,asassessedbywaistcircumferencewasagreedasessential"tothediagnosis,basedon"thelikelihoodthatcentralobesityisanearlystepintheetiologicalcascadeleadingtothefullmetabolicsyndrome.
"QuestionshavebeenraisedastotheclinicalutilityofdiagnosingtheMetS,regardlessoftheversionused.
However,ratherthanaddressthisissue,apathophysiologicalapproachwillbetaken,andthefocuswillbeonwhythespecificcomponentsusedinallversionsformaclusterofrelatedCVDriskfactors.
Morespecifically,evidencewillbepresentedthatinsulinresistance,andhowtheorganismrespondstothisdefect,providestheonlycoherentexplanationastowhytheabnormalitiesthatcomprisethecurrentversionsoftheMetSclustertogether.
T4:PLEnvironmentalandcognitivedeterminantsofenergybalance-relatedbehavioursKremers,SPJMaastrichtUniversity,Maastricht,TheNetherlandsStudiesondeterminantsofenergybalance-relatedbehaviourshaveoftenusedisolatedapproaches.
Forexample,theyareeitherbasedonsocial-cognitivemodelsofhealthbehaviourortheyapplyanecologicalapproach.
Anoverviewwillbepresentedofthecurrentempiricalbaseregardingenvironmentalandsocial-cognitivedeterminantsofenergybalance-relatedbehaviours.
Inthispresentation,itisarguedthattheoriginsofenergybalance-relatedbehavioursnecessitateanintegratedapproachinthestudyofbehaviouraldeterminants.
SuchanintegratedapproachisconceptualizedintheEnRGframework(EnvironmentalResearchframeworkforweightGainprevention).
Intheframework,behaviourispostulatedtobetheresultofasimultaneousinfluenceofconsciousandunconsciousprocesses.
'Obesogenic'environmentalinfluencesarehypothesisedtoinfluencebehaviourbothindirectlyanddirectly.
Theindirectcausalmechanismreflectsthemediatingroleofbehaviour-specificcognitionsintheinfluenceoftheenvironmentonbehaviour.
Adirectinfluencereflectstheautomatic,unconscious,influenceoftheenvironmentonbehaviour.
Specificpersonalandbehaviouralfactorsarepostulatedtomoderatethecausalpath(i.
e.
,inducingeithertheautomaticorthecognitivelymediatedenvironment–behaviourrelation).
Exampleswillbepresentedregardingthepotentialadditionalvalueofapplyinganintegratedapproach.
Itmayguideresearchtowardscausalmechanismslinkingspecificenvironmentalfeatureswithenergybalance-relatedbehavioursindistinctpopulations.
Futureperspectivesarediscussedintermsoftheevolutionofaparadigmthatmayhelptodisentangletheroleof'obesogenic'environmentalfactors.
T5:PLHowtoputthebrakesontheobesityepidemicSwinburnBAWHOCollaboratingCentreforObesityPrevention,DeakinUniversity,Melbourne,AustraliaItissurprisingthatatanindividualandpopulationlevel,obesityisnotonlypersistentbutincreasingdespitetheapparentlypowerfulbrakesofsufficientknowledgeaboutcausesandsolutions,strongsocialprejudiceagainstobesity,personallossofqualityoflife,andevenphysiologicalresponsesagainstweightgain.
Highlyobesogenicenvironmentsbackedbystrongcommercialdriversandviciouscycleswhichtrappeopleintheobesestatehelptoexplainthisparadox.
Asocietalapproachwillbeneededtoreducetheobesityepidemicandinparticulartocurtailthecommercialdriversofoverconsumption(especiallyovereatingandcardependence).
Thiswillrequirepoliticalleadershipandapolicybackbonetosupporton-the-groundprogramsandsocialmarketing.
Unfortunately,theinitialpoliticalresponsesinternationallyhavebeentoimplementtheprograms(ofteneducational)withoutthepolicy.
Policyoptions,includingregulationsrestrictingfoodmarketingtochildrenandchangingfoodsupplypoliciesandrelatedfiscaldrivers,willbeveryimportant.
Community-basedprogramscanpotentiallycreatetheirown'epidemics'ofhealthyeatingandphysicalactivityastheytakeownershipoftheproblemandteacheachotheraboutcreatingsolutions.
Itislikelythatmanyofthesolutionsforobesitywillcomefromactiontotackleothersocietalissueswithclimatechange,trafficcongestion,andurbanliveabilitybeingthemostlikelysourcesof'stealth'interventionsforobesity.
Therearefewexamplesinternationallyofreversalsofobesity,butitislikelythathigherincome,youngerwomeninwealthycountrieswillbethefirstsub-populationtoshowreductionsinobesityprevalence.
- timeswww.8090.com相关文档
- russiawww.8090.com
- VOLmaxwww.8090.com
- Dysfunctionwww.8090.com
- 理财www.8090.com
- 固原市www.8090.com
- 31个省级地区国家重点监控企业自行监测信息公开平台及污染源监督性监测信息公开网址
Megalayer(48元)新增 美国CN2优化线路特价服务器和VPS方案
Megalayer 商家算是新晋的服务商,商家才开始的时候主要是以香港、美国独立服务器。后来有新增菲律宾机房,包括有VPS云服务器、独立服务器、站群服务器等产品。线路上有CN2优化带宽、全向带宽和国际带宽,这里有看到商家的特价方案有增加至9个,之前是四个的。在这篇文章中,我来整理看看。第一、香港服务器系列这里香港服务器会根据带宽的不同区别。我这里将香港机房的都整理到一个系列里。核心内存硬盘IP带宽...

819云互联 香港 日本 美国 2核4G 18元 8核8G 39元 免费空间 免费CDN 香港 E3 16G 20M 230元/月
819云互联是海外领先的互联网业务平台服务提供商。专注为用户提供低价高性能云计算产品,致力于云计算应用的易用性开发,并引导云计算在国内普及。目前平台研发以及运营云服务基础设施服务平台(IaaS),面向全球客户提供基于云计算的IT解决方案与客户服务,拥有丰富的海外资源、香港,日本,美国等各国优质的IDC资源。官方网站:https://www.819yun.com香港特价物理服务器:地区CPU内存带宽...
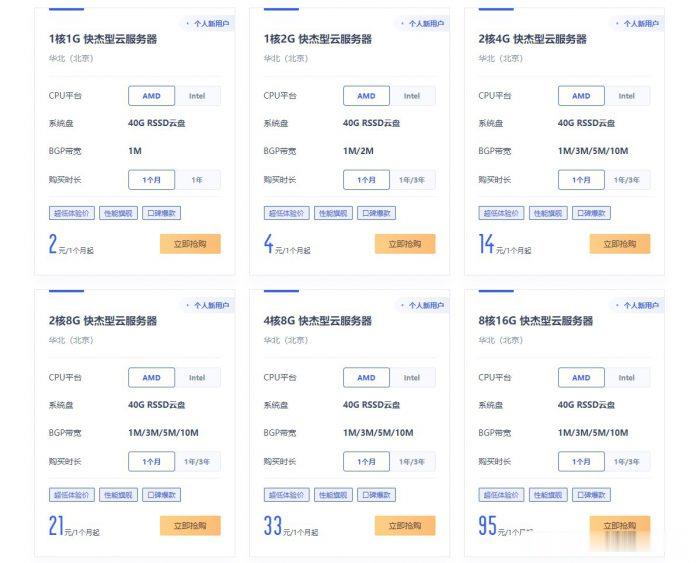
ucloud国内云服务器2元/月起;香港云服务器4元/首月;台湾云服务器3元/首月
ucloud云服务器怎么样?ucloud为了扩大云服务器市场份额,给出了超低价云服务器的促销活动,活动仍然是此前的Ucloud全球大促活动页面。目前,ucloud国内云服务器2元/月起;香港云服务器4元/首月;台湾云服务器3元/首月。相当于2-4元就可以试用国内、中国香港、中国台湾这三个地域的云服务器1个月了。ucloud全球大促仅限新用户,国内云服务器个人用户低至56元/年起,香港云服务器也仅8...
www.8090.com为你推荐
-
sonicchat国外军人的左胸上有彩色的阁子是什么意思安徽汽车网安徽什么汽车网站比较好?西部妈妈网加入新疆妈妈网如何通过验证?haokandianyingwang有什么好看的电影网站336.com求一个游戏的网站 你懂得125xx.com115xx.com是什么意思haole10.comwww.qq10eu.in是QQ网站吗www.vtigu.com如图所示的RT三角形ABC中,角B=90°(初三二次根式)30 如图所示的RT三角形ABC中,角B=90°,点p从点B开始沿BA边以1厘米每秒的速度向A移动;同时,点Q也从点B开始沿BC边以2厘米每秒的速度向点C移动。问:几秒后三角形PBQ的面积为35平方厘米?PQ的距离是多少抓站工具仿站必备软件有哪些工具?最好好用的仿站工具是那个几个?lcoc.top服装英语中double topstitches什么意思